Shobana Radhakrishnan
|
October 24, 2026
|
6
min read
The protein-hormone connection: How it supports metabolism, appetite
Some hormones are made from amino acids. Some others rely on raw materials from protein to circulate in blood
Read More
Protein is associated with the building of muscle, tissue repair and the maintenance of bodily strength. But its role extends beyond these functions. “Almost every function in our body depends on protein in some way. It helps the body produce certain hormones, transport them through the bloodstream, and regulate processes involved in metabolism, appetite and reproduction,” says Dr. Janani Subburaj, an integrative lifestyle practitioner and founder of YogAhara Wellness.
Proteins are made up of smaller units called amino acids. All nine essential amino acids–which the body cannot produce in sufficient quantities–must be obtained through food. Amino acids from dietary protein provide the raw materials needed to synthesise hormones and other proteins involved in endocrine function.
The amino acid pool is a dynamic supply of free amino acids in the blood and tissues. It is typically replenished by dietary protein breakdown, the breakdown and recycling of existing body proteins, and the body's synthesis of non-essential amino acids. Cells use these amino acids to build specific proteins through transcription, in which DNA instructions are copied into messenger RNA (mRNA), and translation, in which ribosomes read the mRNA instructions and link amino acids together using peptide bonds.
Some hormones are made from amino acids, either by modifying a single amino acid or by joining several amino acids into chains through protein synthesis. For instance, insulin, produced by the pancreas, is a protein hormone that helps regulate blood glucose. Insulin-like growth factor 1 (IGF-1), which supports growth and tissue repair, and thyroid-stimulating hormone (TSH), which signals the thyroid gland to produce thyroid hormones, are also protein-based hormones.
Hormones need to travel from the organs that produce them to the tissues where they act. Certain proteins help transport them through the bloodstream. “Think of the bloodstream as a transport network. Thyroid hormones, for instance, bind to proteins such as thyroxine-binding globulin. Steroid hormones, including oestrogen, testosterone and cortisol, also circulate mostly bound to transport proteins,” says Dr. Janani.
Transport proteins influence how hormones circulate and how long they remain in the bloodstream.
These transport proteins influence how hormones circulate and how long they remain in the bloodstream. Since the body synthesises these proteins using amino acids, adequate protein intake contributes to their production.
“When protein and overall food intake are inadequate for a prolonged period, we may see loss of muscle, reduced strength, poor growth in children, slower recovery from illness, and, in case of severe malnutrition, swelling of the feet or legs and changes in hair or skin,” says Dr. Sakthivel Sivasubramanian, Consultant Endocrinologist and Lifestyle Physician at The Hormone Clinic, Tiruchirappalli.
Also read: Is your body low on protein? Signs and impacts of a deficiency
The body must also activate and process hormones once they are transported and reach their target cells or tissues–so the hormones can perform their functions. The thyroid gland produces mainly thyroxine (T4), which is converted into triiodothyronine (T3), the more biologically active form in many tissues. T3 helps regulate metabolism and body temperature.
“This conversion depends on enzymes called deiodinases, which are proteins that require selenium to function properly. Amino acids from dietary protein help the body produce these enzymes, making adequate nutrition important for normal thyroid hormone activity,” notes Dr. Janani.
Protein also plays a key role in blood glucose regulation by slowing carbohydrate digestion, stimulating the release of insulin and hormones such as GLP-1, and providing amino acids that the body can gradually convert into glucose without causing a sharp blood sugar spike. “Think of protein as a speed breaker,” explains Dr. Janani. A balanced meal containing protein, carbohydrates and fibre can moderate the rise in blood glucose after eating. Insulin and glucagon, two hormones produced by the pancreas, regulate blood glucose. Insulin helps glucose move into cells, while glucagon helps make glucose available to the body between meals.
Think of protein as a speed breaker.
Amino acids from protein-containing meals can stimulate the release of both. Consuming protein increases amino acid levels in the blood, stimulating pancreatic beta cells to release insulin and alpha cells to release glucagon. Insulin helps the muscles use amino acids to build tissue, while glucagon signals the liver to convert excess amino acids into glucose, thus preventing blood sugar levels from dropping too low.
Protein also influences appetite-regulating signals. Ghrelin, often called the hunger hormone, signals the brain when it is time to eat. Leptin, produced mainly by fat cells, regulates the body’s energy balance and appetite in the long term. “A protein-rich meal tends to lower ghrelin and raise fullness signals (an indication of satiety) such as GLP-1 (glucagon-like peptide-1) and PYY (peptide YY). This is one reason why meals such as eggs with wholegrain toast, or dal with rice and vegetables may keep us satiated for longer than a meal consisting largely of refined carbohydrates,” says Dr. Janani.
“The overall response depends on a balanced meal and the person's health; it is not as simple as ‘the more the protein, the better the blood sugar’,” notes Dr. Sakthivel.
Also read: Protein’s seen and unseen benefits: How it affects metabolism, muscle repair
Protein also supplies amino acids involved in processes that influence mood and sleep. One example is tryptophan, an essential amino acid that the body uses to produce serotonin, a neurotransmitter involved in mood regulation. Serotonin is also a precursor to melatonin, the hormone that helps regulate the sleep-wake cycle.
Adequate protein intake supplies the amino acids needed for these processes, although mood and sleep are also shaped by factors such as stress, physical activity and light exposure (light regulates your body’s internal clock, or circadian rhythm. While protein provides amino acids like tryptophan to make brain chemicals, light helps regulate the timing of processes such as melatonin production and sleep).
Reproductive health depends, among other things, on communication between the brain and reproductive organs, coordinated through a network of hormones. In women, follicle-stimulating hormone (FSH) and luteinising hormone (LH), both produced by the pituitary gland, help regulate ovarian function, including follicular development and ovulation. These protein-based hormones form part of the hypothalamic-pituitary-ovarian axis, which coordinates signals between the brain and ovaries.
Oestrogen and progesterone, meanwhile, are steroid hormones made from cholesterol rather than directly from dietary protein. However, the enzymes involved in their synthesis–such as aromatase, which helps convert androgens into oestrogens, and 3β-hydroxysteroid dehydrogenase, which helps produce progesterone–are proteins. Transport proteins, such as sex hormone-binding globulin and albumin, also help carry these hormones through the bloodstream.
Very low protein intake, especially when the body does not get enough energy from food, can disrupt hormonal signalling between the brain and ovaries, potentially contributing to irregular or missed periods, says Dr. Janani. However, menstrual irregularities can have several causes, including stress, excessive exercise, pregnancy and underlying medical conditions. They should not automatically be attributed to protein deficiency.
Also read: Why your body may not be optimising the protein you eat
A national survey done by ICMR–INDIAB reveals that the typical Indian diet derives a massive 62.3% of its energy from low-quality carbohydrates and only 12% from protein. While studies have established the metabolic links between protein and macronutrient imbalances and disruptions to insulin, thyroid function, and satiety signaling, experts have said that a well-balanced diet along with other factors play a role in hormonal imbalance.
"Consuming adequate protein is just a part of the puzzle as overall health status, nutrition intake, sleep, lifestyle and stress also matter when it comes to hormone balance, supporting immunity, managing mood or supporting reproductive health," notes Aditi Prabhu, a nutritionist.
Although protein supports normal hormonal function, inadequate protein intake is only one of several factors that can cause it. Fatigue, weakness and other symptoms may also be associated with nutritional deficiencies, stress or underlying medical conditions.
Consuming adequate protein is just a part of the puzzle as overall health status, nutrition intake, sleep, lifestyle and stress also matter.
“The body can often maintain hormone production despite variations in protein intake, and symptoms of protein deficiency usually overlap with those of other nutritional deficiencies and illnesses,” says Dr. Kavitha Muniraj, Medical Director, Senior Consultant - Endocrinology, Samatvam Diabetes Centre, Bengaluru.
Severe protein deficiency, particularly when accompanied by inadequate calorie intake, can interfere with normal growth and metabolism. “For instance, prolonged undernutrition can lower IGF-1 levels, even when the growth hormone is present,” Dr. Kavitha explains.
Increasing protein intake is not a treatment for thyroid disease, diabetes or other endocrine disorders. “The goal is adequate protein, not automatically a high-protein diet,” notes Dr. Sakthivel.
Cover art by Pratik Bhide

Walk into an urban pharmacy and browse the protein bar aisle, and you’ll increasingly find products built around collagen, marketed as easy ways to boost your protein intake. Some prominently display their protein content alongside claims about improving skin, hair, joints or muscle recovery.
For consumers trying to eat more protein, the message seems straightforward: collagen is protein, so a collagen bar must be a protein bar. But while collagen is indeed a protein, it is not nutritionally interchangeable with the proteins found in foods such as eggs, dairy, soy, or meat.
The difference comes down to what each type of protein actually does in the body, and the amino acids it provides.
When we consume protein, our digestive system breaks it down into amino acids, which the body uses to build and repair proteins. Of the 20 amino acids used by the body, nine are considered essential because we cannot make them ourselves and must obtain them from food.
Collagen is the body's major structural protein and is abundant in skin, bones, cartilage, tendons and ligaments. A ‘complete’ protein contains all nine essential amino acids in adequate amounts. Collagen is an incomplete protein since its amino acid profile is mainly composed of glycine, proline and hydroxyproline, all of which are non-essential amino acids. It contains no tryptophan, an essential amino acid which regulates sleep, mood and muscle synthesis; and very little methionine and leucine, which aid in the growth and repair of muscles and tissues.
While collagen is indeed a protein, it is not nutritionally interchangeable with the proteins found in foods such as eggs, dairy, soy, or meat.
That makes collagen an unusual, if impractical protein supplement. For starters, collagen is found naturally only in tougher cuts of red meat and the bones and skin of fish like tilapia and salmon. Its molecules (whether from whole foods or supplements) are also too large and tightly bound to be absorbed directly into the body. The gut breaks it down into individual amino acids and short chains of amino acids called peptides. This means that even though products may be marketed as collagen ‘supplements’ or ‘boosters,’ our bodies don’t preserve these distinctions and utilise them as is. The amino acids from a collagen supplement may be routed to wherever our bodies deem necessary at the moment—perhaps for cartilage or bone integrity, or for the keratin in our hair.
Another significant reason why this protein is not the most nutritionally efficient supplement, is because a large share of its amino acids are ones the body can produce itself. Simultaneously, it is deficient in amino acids that the body cannot make and must obtain from food. So although collagen contributes to the total number of grams of protein consumed, those grams are not nutritionally equivalent to the same amount of a protein rich in indispensable amino acids.
A large share of its amino acids are ones the body can produce itself.
This distinction matters especially when collagen is used as the main protein in a supplement or food marketed to people trying to increase their protein intake. Ten grams of collagen still count as ten grams of protein on a nutrition label. But they do not deliver the same amino-acid package as ten grams of a complete protein like whey, milk, egg or soy.
Also read: The human body needs collagen. Does it need collagen supplements?
The Protein Digestibility Corrected Amino Acid Score (PDCAAS) is one standard method used to measure protein quality. It first compares the amount of each essential amino acid in a protein, such as collagen, with what the body needs, and identifies the amino acid which is most deficient. This gives the protein its amino acid score, which is then combined with the protein’s digestibility percentage to give the PDCAAS score. This score, expressed as a number between 0 and 1, signifies the quality of any protein consumed after factoring in its amino acid profile and digestibility.
Since the score is ultimately determined by the most deficient essential amino acid, the absence of tryptophan in collagen drives its PDCAAS score to zero. This does not mean it contains zero protein or that the body simply ignores it. But if collagen were your only protein source, its amino-acid profile would be inadequate to meet your body's requirements.
If collagen were your only protein source, its amino-acid profile would be inadequate to meet your body's requirements.
If a collagen bar claims to ‘boost’ protein (especially for people building muscle), it is important to consider how much of that protein comes from collagen alone and whether it is complemented by other protein sources. If a collagen supplement’s primary selling point is that it boosts protein intake, the promise deserves a closer look: the number on the label does not tell you the quality of the protein behind it.
For someone simply looking to eat more protein, foods such as dairy, eggs, soy, pulses, fish and meat provide a broader mix of indispensable amino acids. Collagen may have a place of value for other reasons, but as a protein supplement, its appeal should not rest on the word ‘protein’ alone.
Also read: Protein’s seen and unseen benefits: How it affects metabolism, muscle repair
Walk into any pharmacy in urban India, or scroll through videos from wellness influencers on social media, and you'll find powders, gummies and drinks promising to boost your collagen. When placed conspicuously at billing counters, much like bubble gum and candy used to be a decade ago, customers are prompted to make a last-minute collagen purchase. More protein bars now list it as an ingredient, too, touting its benefits for healthy skin, bones and joints. Propelled by these claims, India’s market for these products stood at nearly $65 million in 2024. Recently, ‘vegan collagen’ has joined the growing list of offerings in this segment of the supplement market. The name, however, can be misleading: plants do not contain collagen.
It is the most abundant protein in the human body, making up about 30% of our total protein. But we don’t simply absorb the collagen that we consume directly (from animal sources). So what actually happens to it inside our bodies—and can consuming it via food items or supplements really help us make more of the bodily protein we’re trying to preserve?
We don’t simply absorb the collagen that we consume directly.
Imagine your body as a suspension bridge. The steel cables aren't glamorous—you notice them only when they fray—but without them, the bridge begins to weaken. Collagen is one of those cables.
Specialised cells in our bodies called ‘fibroblasts’ are responsible for synthesising it. They act like protein factories, linking together amino acids (primarily glycine, proline and hydroxyproline) to make collagen. Collagen molecules are rope-like structures which can withstand a lot of stress. This makes them the perfect scaffolding for our bodies, giving tendons their tensile strength, bones much of their framework, and cushioning cartilage.
What consumers often get wrong is that this protein is not simply a tank that you can refill. “Collagen is not a single substance but a family of more than 28 classes, each serving different functions in the body,” says Mumbai-based dermatologist Dr. Manasi Shirolikar. Ingested collagen doesn’t travel intact to the dermis; its molecules are too large to pass through the skin’s outer barrier. This fundamental nature is why supplements—vegan, or otherwise—are not the answer to boosting its reserves. Our body cannot digest whole, native collagen ‘as is.’

Natural collagen molecules (from food, or supplements) are enormous and tightly bound. Digestive enzymes like pepsin break them down into individual amino acids and di/tri-peptides (chains of two and three amino acids respectively), says Dr. Shirolikar. This is why most oral supplements are in the form of hydrolysed collagen (or collagen peptides), where the collagen has already been artificially broken down into tiny chains, so your gastrointestinal tract can digest and absorb it much more efficiently. However, even these contain peptides too large for direct absorption into your skin or joints.
Collagen molecules are rope-like structures which can withstand a lot of stress. This makes them the perfect scaffolding for our bodies.
Even though supplements may be marketed as collagen builders, our bodies don’t preserve these distinctions. The acid in our gut denatures these molecules, rerouting them wherever necessary, perhaps to make keratin for our hair. Or the peptides may form collagen that gets deposited in other parts of the body, such as cartilage, bone, muscles, or tendons. It’s not necessarily going to manufacture the collagen that gives us the glowing skin we’re pinching our wallets for.
Also read: Whey to go: A complete guide to protein
The beauty industry’s fascination with collagen began in the late 1990s and early 2000s, when it first appeared as an ingredient in skin creams and serums, touted to enhance elasticity. However, its effectiveness as a topical (directly on the skin) application was doubted by dermatologists early on, as collagen is not naturally found on the skin’s surface but in the deeper layers. Skincare products containing collagen only temporarily moistened and plumped up skin, appearing to reduce fine lines and wrinkles. People continue to be drawn to these products possibly because a structural protein is marketed as a shortcut to a youthful appearance. These marketing claims are ambitious at best, and ridiculous at worst (some promise to improve skin ‘texture’ by up to 42%!). Elasticity aside, they are promoted as a way to reduce fine lines, improve hydration, brighten the complexion, or even thicken hair.
Your body doesn't need collagen from food to produce collagen. It needs the raw materials and the right nutrients.
Collagen is found naturally only in animal connective tissue. Foods richest in collagen include tougher cuts of red meat, as well as the skin and bones of freshwater and saltwater fish. Bone broth and gelatin, made by simmering animal bones with a little vinegar for several hours, are often promoted as health foods. ‘Vegan’ collagen then, is largely a marketing gimmick, and has become a buzzword because it promises to cater to India’s large vegetarian demographic.
What slips unnoticed is that these supplements are labelled as ‘boosters’ or ‘builders.’ They contain plant-derived amino acids (glycine, proline, lysine) plus cofactors (helper molecules) like vitamin C, copper, zinc, silica, and at times, hyaluronic acid. “They contain zero actual collagen,” Dr. Shirolikar clarifies.
So do vegetarians get only limited access to the fountain of youth? “Definitely not,” affirms Dr Shirolikar. "Your body doesn't need collagen from food to produce collagen. It needs the raw materials and the right nutrients." It is always built from scratch inside the body (since both builders and collagen from whole foods are broken down into a common pool of amino acids). To do this, it first needs enough dietary protein to supply amino acids, which can come from legumes, grains, soy, nuts, seeds, dairy or eggs.
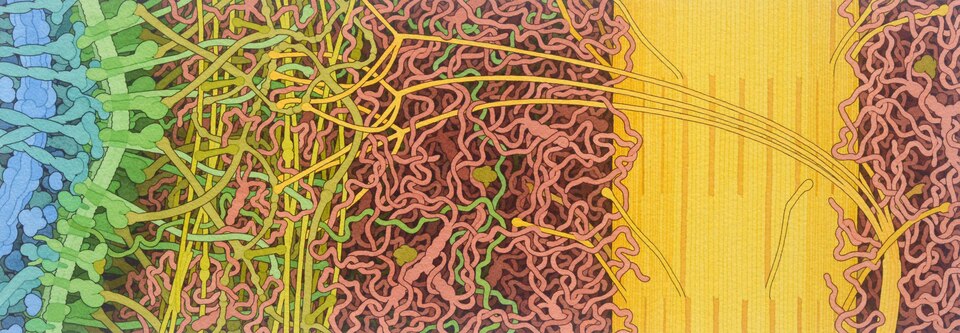
To make collagen, the body also depends on vitamin C, an essential cofactor that supports the enzymes stabilising the newly formed collagen fibres by modifying proline and lysine. Without enough vitamin C, collagen is produced but remains weak and unstable—the underlying mechanism behind scurvy. Minerals such as copper, zinc and manganese also support different stages of formation and cross-linking. “As long as you're meeting your protein and micronutrient needs, your body can make perfectly healthy collagen—even if you've never eaten it in your life,” Dr Shirolikar adds.
Also read: Insulin, explained: The lock-and-key mechanism controlling blood sugar
What justifies a continued interest in supplements, Dr. Shirolkar explains, is this: “Collagen hydrolysate delivers an unusually glycine/proline/hydroxyproline-rich amino acid pool that ordinary dietary protein doesn't replicate as efficiently.” Some of these peptide chains resist being broken down into individual amino acids and may act as ‘signalling molecules.’ That is, “they may reach dermal fibroblasts in our body and stimulate them to produce more collagen and hyaluronic acid,” she adds.
Most people forget that a decline in collagen is a natural outcome of aging. Production declines by roughly a percent every year, starting from the mid-twenties. Any pill purporting that it can magically fill that ‘tank’ should be taken with a grain of salt. There’s some early, encouraging research, but a lack of randomised controlled trials (which are the gold standard for testing dietary supplements); in any case, there is not enough knowledge to substantiate the rapidly growing collagen market in India and across the world. Many of these supplements are not vetted by state drug administrations. Moreover, several studies are funded by the very nutraceutical companies who stand to gain by expanding the collagen market.
Marine collagen supplements (extracted from the skin, scales and bones of fish) also come with safety considerations. Fish in polluted waters store heavy metals in their tissues. Supplements derived from seafood may especially be contaminated by methylmercury, which damages the nervous system. Like other dietary supplements, they are not evaluated for safety or effectiveness before reaching the market. Together, these concerns complicate the idea that collagen supplements are both environmentally benign and inherently risk-free.
Dr. Shirolikar’s advice is to stick to the basics that keep our bodies well-oiled every day: using sunscreen, getting enough sleep and smoking less. “If there's one intervention with the strongest evidence for preserving collagen, it's broad-spectrum sunscreen. UV exposure activates matrix metalloproteinases (MMPs)—enzymes that break down collagen, making sun protection the single most effective defence against premature skin ageing.” Adequate dietary protein and micronutrients like vitamin C, zinc and copper may be less glamorous, but they're the essential building blocks for collagen synthesis. Without them, nothing else works as well.
Photoprotection and adequate sleep (during which growth hormone pulses drive tissue repair) have better-established effects on slowing down collagen breakdown than any other oral supplement. Supplements are reasonable to try, but evidence to their benefits is modest and inconsistent, Dr. Shirolikar says. They shouldn’t replace the fundamentals!
The most accurate way to think about collagen supplements is that they don't replace lost collagen or become skin collagen. At best, they may provide some of the ingredients—and perhaps some molecular signals—that support your body's own collagen factory. Everything else still depends on the same fundamentals: protecting collagen from damage, eating enough protein and getting the nutrients needed to build it in the first place.
Also read: In an age of food abundance, why does ‘hidden hunger’ hold India back?
Edited by Anushka Mukherjee and Neerja Deodhar
Slider Credit: NIH Photo Gallery via Wikimedia Commons
For ages, women have learnt to live with inexplicable changes in their bodies in a state of resigned acceptance. They often repress the anxiety that arises from signs of unfamiliarity. Consulting a doctor is an afterthought that comes too late. This is reinforced by social conditions that pay scant attention to women’s health, creating a cascading effect of flawed assumptions about symptoms, late diagnoses and erroneous treatment.
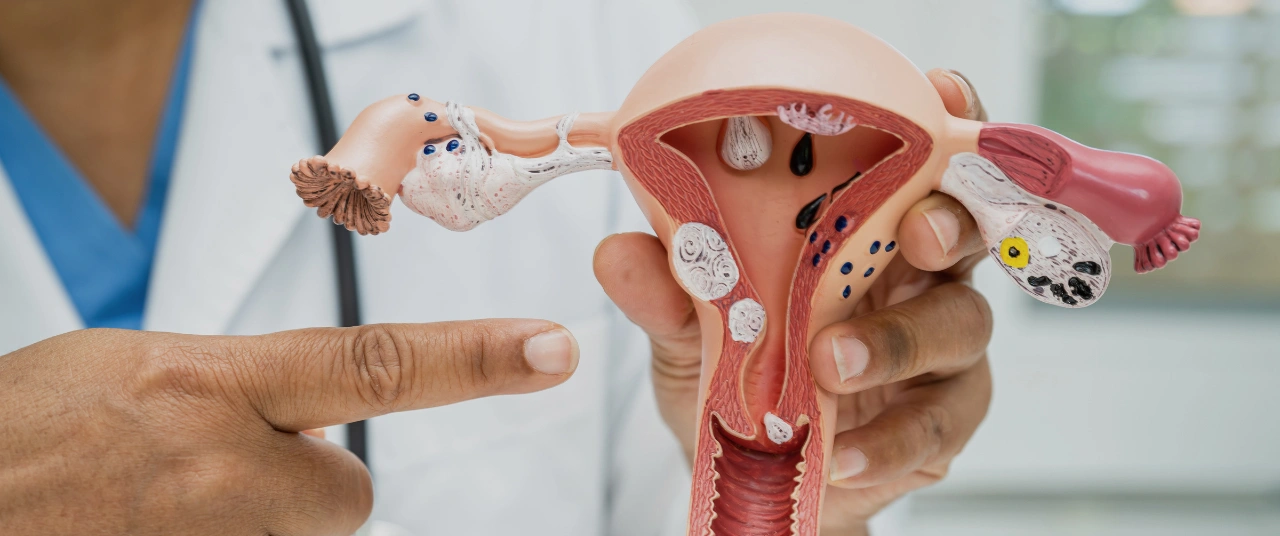
One of the most pronounced examples of this lived medical reality is the Polycystic Ovary Syndrome (PCOS), a hormonal and metabolic disorder that has affected, by global estimates, 170 million women. The all-too-common disorder occurs when the ovaries produce excess hormones called androgens, which manifest in symptoms like irregular menstrual cycles, excessive acne or hair growth, or enlarged ovaries. Worryingly, a patient with no pronounced symptoms can also be diagnosed with the condition.
For a disorder so vastly prevalent, its constellation of physical and psychological symptoms has, for long, hindered a thorough comprehension of its underlying nature. Over nine decades after the term was first coined, a global congregation arrived at the consensus that “PCOS” does little to reflect the range of complications found in persons living with this condition. In May 2026, Polycystic Ovary Syndrome was officially renamed Polyendocrine Metabolic Ovarian Syndrome (PMOS). This new terminology was the result of a 14-year-long process organised by 56 academic, patient and clinical organisations.
The engagement involved two global surveys that recorded 14,360 responses from patients and health professionals, group workshops and market analysis to arrive at an agreement as to whether PCOS needed a new name and if it did, to pick a most suitable replacement. Part of the process relied on the Delphi method—questionnaire-based surveys to gather consensus from participants with domain expertise in a given subject—to arrive at a conclusive redefinition. The health professionals who participated in the surveys represented a wide range of disciplines including gynaecology, reproductive endocrinology, nutrition and nursing.
The terms “polyendocrine” and “ovarian” stood out as potential alternatives in the survey results. A workshop held in February 2026 settled on the new term. Only two participants did not support a name change. In a paper detailing the process to rename the condition, The Lancet stated that the transition to the usage of PMOS across the board is estimated to take three years of time.
“The current name reflects only one organ and fails to capture the disorder’s multisystem nature,” reads the paper authored by the researchers who led the process. A patient with PMOS can show symptoms that concern endocrine, metabolic, reproductive, psychological and dermatological features. The old term gave the misleading idea that the condition should necessarily entail the presence of cysts in ovaries, when in reality, irrespective of the presence of cysts, a patient can be diagnosed with the condition due to the evidence of other symptoms. Besides, the old term resulted in disproportionate emphasis on pregnancy-related concerns. “The reproductive focus of the name can reinforce stigma, particularly in sociocultural contexts where fertility carries high value,” the authors said.
PMOS patients, and doctors across specialties who have been treating this disorder, have widely welcomed the new terminology. “It helps to specify what exactly is the clinical diagnosis. The ovaries are only one part and not the whole disease on its own,” says Dr. Aakanksha Padma Naik, a Mumbai-based gynaecologist. The term PCOS, she says, suggested that cysts in the ovaries “was the only point that mattered”.
While references to symptoms in the ovaries can be traced back to medical texts of the 19th century, the first significant breakthrough in characterising PCOS is attributed to Irving Freiler Stein and Michael Leo Leventhal, two American gynaecologists. In 1935, at a meeting of the Central Association of Obstetricians and Gynaecologists, Stein and Leventhal described the clinical histories of seven women with symptoms including irregular periods, hirsutism (excessive hair growth in a male pattern) and infertility. They also reported that the seven women had enlarged ovaries. The paper presented by the two doctors was titled “Amenorrhea associated with bilateral polycystic ovaries”, elaborating on the formation of multiple cysts–fluid-filled sacs–in the ovaries, causing them to become enlarged and painful. Amenorrhea denotes the absence of menstruation.
Besides, the old term resulted in disproportionate emphasis on pregnancy-related concerns.
PCOS has since been a subject of extensive research in modern medicine, evolving to acknowledge that its diagnosis cannot be confined to symptoms in the ovaries. A milestone in the study of this disorder arrived in 2003 when 27 medical experts gathered in Rotterdam, Netherlands for a conference to come up with a revised criteria to diagnose it. The guidelines that are now known as the Rotterdam criteria stipulate that a patient can be diagnosed with PCOS if two of these three features are found: oligo-anovulation, that is infrequent or absent ovulation; hyperandrogenism characterised by an excess production of androgens which are hormones typically associated with male physiological characteristics; polycystic ovaries, that is, the presence of 12 or more follicles–small sacs containing immature eggs–in each ovary measuring 2-9 mm in diameter and/or an ovarian volume exceeding 10 ml. This consensus at Rotterdam expanded the definition of PCOS and became the widely accepted standard to confirm the diagnosis of this condition.
Also read: Health taxes are no silver bullet. But they are a step in the right direction
The new term—Polyendocrine Metabolic Ovarian Syndrome—decentres the ovaries and represents the disorder’s character as one that affects diverse aspects of the body. The endocrine system is responsible for creating and releasing hormones that regulate various bodily functions. The new name draws focus towards hormonal imbalance and metabolic dysfunction that characterise the condition.
For instance, resistance to insulin, a hormone that regulates blood sugar, is commonly observed in patients diagnosed with PMOS. This may result in hyperinsulinemia—the body’s response of overproducing insulin to keep blood sugar levels stable. The high-insulin state can stimulate the ovaries to produce excess androgens, which in turn triggers insulin resistance, furthering a vicious cycle that disrupts multiple bodily functions. The new term is meant to reflect such interactions between endocrine and metabolic abnormalities.
PMOS is not just a gynaecological concern, but a syndrome that needs to be treated by a cross-section of specialists
Dr. Naik says that irrespective of the name change, gynaecologists were already following the practice of referring patients with symptoms such as insulin resistance to doctors specialised in endocrinology. “With the change of name, patients are more likely to see and understand the diagnosis versus just us understanding it,” she says. Earlier, she says, when gynaecologists referred patients to an endocrinologist or recommended that they undergo a series of tests to check hormone levels, patients were often sceptical of its necessity. If they approached a gynaecologist to address their irregular menstrual cycle, they were puzzled as to why they were being asked to test their insulin levels. With the new term, Dr. Naik hopes that patients will comprehend that PMOS is not just a gynaecological concern, but a syndrome that needs to be treated by a cross-section of specialists.
“When you look at ‘polycystic ovaries’, people think that it is all about cysts in the ovaries,” says Dr. Anurag Lila, an endocrinologist, adding that patients were mainly concerned with the status of the cysts, requesting an ultrasound to see whether they have grown or reduced. “The disease is much beyond that,” Dr. Lila says.
Also read: Insulin, explained: The lock-and-key mechanism controlling blood sugar
The disruption of the Hypothalamic-Pituitary-Gonadal axis, the endocrine system that functions through a complex feedback loop between hormone-producing glands, is a key factor underlying PMOS. To diagnose or rule out PMOS, an endocrinologist examines the hormonal levels which in turn reflect the extent of risk of diabetes, gestational diabetes, and dyslipidemia (abnormal levels of lipids or fats in the bloodstream).
Dr. Lila opines that there is no reason for a delay in diagnosing PMOS regardless of the specialist consulted by a patient. A gynaecologist, endocrinologist or dermatologist, he says, can identify symptoms associated with the condition. “There are difficulties in managing it because like in any disorder such as obesity or weight gain, it is not easy to make lifestyle changes,” he says.
PMOS, as Dr. Lila put it, is not owned by any one branch of medicine. “If we try to make a strict compartmentalisation, it will be wrong. It is a team of doctors who manage it.” If the symptoms manifest in hirsutism, for example, a dermatologist steps in to treat it. Likewise, only a mental health professional can address the depression or anxiety that a PMOS patient may be coping with. “It is a multisystem disorder that affects you at multiple levels. The treatment and the modality changes at every stage of its management,” Dr. Lila says.
Women live with the symptoms of PMOS for much of their lives, and a balanced diet is critical to keeping them in check. But there is no one-size-fits-all approach, says nutritionist Aditi Prabhu. “Each case has to be handled with care and personalised based on individual goals, current symptoms, health complaints, root cause analysis, medical history, blood reports, lifestyle patterns, sleep habits, stress levels, mental health and their overall relationship with food, especially if they have had any previous experience with dieting,” she says. Broadly, whole grains and pulses, protein sources, a variety of fruits and vegetables, fibre and omega-3-rich foods are part of the diet plan that Prabhu charts for her patients.
Patients grappling with PMOS can grow conscious of their body image. “A lot of women are constantly under the pressure of losing weight, as they are repeatedly made to believe that losing weight is the only solution,” says Prabhu. Enforcing this as the one-stop solution is a trivialisation of a complex condition that manifests differently in each patient. Even a woman with a regular menstrual cycle and optimal weight, Prabhu points out, can struggle with other PMOS symptoms such as mood swings, insulin resistance or metabolic dysfunction.
This name change will not make a major impact unless it is also accompanied by changes in the way this condition is diagnosed, treated and communicated to patients
Insulin resistance heightens the risk of diabetes in PMOS patients. Irregular diet, poor sleep patterns, inflammation, increased fat percentage, chronic stress accelerates sensitivity to insulin. “Early screening and managing it before it worsens can help reduce the risk of diabetes in the long term,” the nutritionist says. Insulin resistance and other symptoms of this condition can be significantly improved if the patient consistently follows recommended dietary and lifestyle changes.
Like many healthcare professionals, Prabhu agrees that the new terminology is a “more holistic representation of the condition”. But it can only go so far in translating into positive practical implications. “This name change will not make a major impact unless it is also accompanied by changes in the way this condition is diagnosed, treated and communicated to patients,” she says.
Also read: Fine print nation: Do nutrition labels meaningfully inform Indian consumers?
What happens to the food we eat, once we’ve devoured it and wiped our plates clean? It gets chewed, swallowed, and pulverized, as it passes through the esophagus, stomach, and small intestine. Here, at long last, the delicious contents of our plates become things the body can use: water, electrolytes, fatty acids, amino acids, and sugars. These components then cross over from the small intestine into the bloodstream, through a variety of processes, to be utilised by different organs.
Given the largely carbohydrate-based Indian diet, the sugars are the largest end product of digestion, and the primary providers of energy. This sugar can be galactose or fructose, but largely, it is glucose.
Glucose lying around in the blood is bad for us.
There's just one tiny problem: our bodies cannot use all that glucose (or other building blocks like amino acids and fatty acids) all at once. While some is consumed by hungry cells immediately, the rest is stored either as glycogen in liver and muscle cells, or as triglyceride in fat cells. This is, in part, a simple rationing exercise; one cannot use up all energy stores in one go.
But it is also a matter of safety. Glucose lying around in the blood is bad for us. Professor and Head of Department of Physiology at Navi Mumbai’s D.Y. Patil Medical College, Dr. Vivek Nalgirkar explains why: "In the short term, the glucose gets converted to fat and causes weight gain. In the long term, it irreversibly binds with protein structures (like skin) in the body, weakening the body and accelerating ageing." So, glucose needs to be packed away safely.
The pancreas, tucked right behind the stomach, is responsible for detecting this excess glucose, and kickstarting the storage process. Gathered in small clusters of the organ are specialised cells called beta cells, which pick up on the high glucose levels in the bloodstream and release insulin. This hormone acts like a key, opening the doors (insulin receptors) of liver, muscle, and fat cells, and ushering glucose inside them. It was first isolated in 1921, and shortly after, in January 1922, it was administered as part of diabetes treatment for the first time.
Naturally, there are times (for example, when you skip lunch) when the body needs to dig into its glucose reserves. For this, the pancreas has a different set of specialised cells called alpha cells. They look out for low glucose levels in the bloodstream (i.e. when glucose is gone) and release a hormone called glucagon. Glucagon opens the doors in the reverse fashion, emptying glucose from the cells they are stored in, and back into the bloodstream.
Together, insulin and glucagon ensure that the blood sugar levels remain constant in the body. Too little (hypoglycemia), and your body—your brain especially—buckles under the lack of energy; too much (hyperglycemia), and the excess energy wreaks havoc on your organs.
Trouble begins to brew when insulin does not work like it is supposed to. Sometimes, the immune system thinks that the beta cells responsible for making insulin are dangerous, and destroys them. This results in Type 1 diabetes and requires patients to take insulin supplements.
The more common condition, however, is Type 2 diabetes, where the body becomes insulin-resistant. The beta cells continue to make and release insulin, but the hormone is no longer able to open the muscle, fat, or liver cells and pack away the glucose. "Think of it like trying to open a rusted lock," says preventative diabetologist Dr. Jagruti Parikh. "Naturally, the door won't open.” The ‘rusting’ happens because of harmful compounds that form when fats or proteins react with excess blood glucose, and can be triggered due to various factors like excess fat, infections, or stress.
This hormone acts like a key, opening the doors of liver, muscle, and fat cells, and ushering glucose inside them
Insulin resistance contributes to obesity through various ways. Firstly, the beta cells can continue to sense excess glucose in the blood, and release higher quantities of insulin to try to counteract it. This upsets the balance that insulin and glucagon concentrations usually maintain, and this high insulin concentration is linked with obesity. Second, since the cells are starving despite abundant glucose in the bloodstream, the brain sends out hunger signals and we end up eating more. Lastly, the liver can struggle to process this extra energy and starts accumulating excess fat inside its cells, resulting in fatty liver disease. Insulin resistance is also a foundational issue causing PMOS (previously termed PCOS/PCOD).
Also read: Food fortification 101: Can foods built in with nutrients counter malnutrition, deficiencies?
The miracle drug of recent times, GLP-1 (which includes the likes of Ozempic), was introduced to control diabetes through weight reduction. GLP-1 stands for glucagon-like peptide-1, and it is a hormone that exists naturally in the body. It acts in the small intestine before digestion is complete. GLP-1 receptor agonists are lab-made medications that are meant to mimic the natural hormone. The first GLP-1 drug was cleared for diabetes treatment by the US FDA in early 2005.
It performs two useful functions for diabetes patients. First, it addresses the issue of excess insulin in blood by restoring the ratio of the hormone to glucagon. "Glucagon is an antagonist (antagonists are substances that block the effect of another substance, or prevent a certain biological response), in a sense. It will normalise the glucagon-to-insulin ratio which is skewed in diabetes patients," says Dr. Nalgirkar. Secondly, GLP-1 reduces hunger at both a biological and psychological level. It affects how the brain ascertains satiety, how quickly the stomach empties food, and even how the liver performs metabolism.
The medication is only prescribed to diabetic patients who match certain diagnostic criteria. "It is never the first line of treatment," says Dr. Parikh. She stresses that GLP-1 drugs are worthless without coordinated changes in lifestyle, otherwise the lost weight will be gained back once the medication is discontinued. Given its prohibitive cost, it is also not a medication most people can afford to take for years together. Dr. Nalgirkar also warns that our understanding of the medication is still in nascent stages.
Also read: Health taxes are no silver bullet. But they are a step in the right direction
GLP-1 drugs find alternate ways to balance blood sugar levels, but there also exists the possibility of reversing insulin resistance. Though the mechanism behind it is not fully understood yet, study after study has proved that exercise and a mindful diet makes our cells more sensitive to insulin, possibly because they increase the number of receptors (locks) on the cell’s surface.
Beneath its 'wonder drug' status, GLP-1 is simply a medication that is prescribed in specific use cases, and approached with the caution of any drug in its early years. In a fat-fearing society such as the one we inhabit, the history and purpose of the medication can serve as an important reminder to not get carried away by its promises of weight loss.
India’s diabetes burden is only growing, with a recent study finding that the country tops the Asia Pacific region in Type 2 diabetes, both in terms of absolute burden and mortality. It is imperative to focus on lifestyle, both diet and exercise, to buck the trend.
Cover art by Pratik Bhide
Also read: Typhoid lurks in India’s water. Why are antibiotics failing to stop it?

June has arrived, and despite the onset of the Southwest monsoons in India, many parts of the country are still waiting for the rains to release us from the clutches of this relentless heat.
It has been a harsh summer for India. On a single day in April 2026, all 50 of the world’s hottest cities were in the country; by May 2026, it housed 97 of the world’s top 100 hottest cities. Andhra Pradesh alone recorded over 300 cases of heatstroke. Though consolidated data on heat-related illnesses are yet to emerge for 2026, India recorded over 7,000 heatstroke cases last year. A 2024 paper also affirmed the prevailing belief that heat-related deaths in India are massively underreported.
Studies suggest that India’s heat events are becoming more frequent and prolonged, though not more intense. From a public health perspective, this means exposure to heat stress for extended periods, without an opportunity to recover from the damage it causes. With recent studies suggesting that heat stress persists in the monsoons as well, it is more important now than ever to understand how the human body responds to heat.
Heat stress occurs when the body cannot adequately dissipate the heat it absorbs from the environment. It is not a single condition but a spectrum. Its earliest manifestations are heat rashes, sunburns, and painful limb cramps. These require only minimal medical intervention, if blisters form on the skin or the cramps become severe.
A heat stroke is the endpoint of heat stress. It is much harder to treat than to prevent
In the next stages, heat stress progresses to cause fainting, heat exhaustion, and finally, heat stroke. Heat exhaustion presents with heavy sweating, body temperature above 38°C (100.4°F), rapid breathing, blurred vision, a weak pulse, and nausea. While suffering from heat stroke, a person becomes dizzy, weak, and acts strangely; their body temperature rises above 41°C (105.8 °F), and their pulse quickens. Any stage after fainting requires medical attention, and heat stroke cases warrant calling an ambulance.
“Many people ignore early symptoms until the condition becomes serious. A heat stroke is the endpoint of heat stress. It is much harder to treat than to prevent,” says Dr. Keerthi Varman M, a General Physician and General Secretary of the Tamil Nadu Resident Doctors Association.
The best way to avoid heat stress is to avoid stepping out or doing strenuous activity during the hottest times of the day, wear loose-fitted clothes, and remain adequately hydrated. In case someone around you is displaying symptoms of heat stress, move the person to a cool area, offer them sips of water, loosen any tight clothing, and fan and spray them with water.
Also read: How the Super El Nino will impact India’s farmers
The human body constantly tries to maintain a stable internal temperature, usually between 36.2 C to 36.7 C (97.3 F to 98.2 F). The hypothalamus acts as the brain’s central thermostat, continuously monitoring core temperature via thermoreceptors in the blood and skin to maintain equilibrium. Under normal conditions, it triggers cooling mechanisms like sweating and vasodilation, or the widening of blood vessels, which allows more blood to flow to the skin, from where it is dissipated into the atmosphere.
When sweating does not work, vasodilation becomes the only way left to cool the body, which puts pressure on the heart vessels.
This system is insufficient in extreme heat events, and becomes inefficient when high temperatures are coupled with high humidity. If the air is already saturated with moisture, sweat will not evaporate. It is this act of evaporation—and not the act of sweating by itself—that cools the body. In just under a decade, India’s average relative humidity has increased from 67.1% to 71.2%, making humidity-related heat stress a rising concern. When sweating does not work, vasodilation becomes the only way left to cool the body, which puts pressure on the heart vessels. This (alongside ozone poisoning) is why excess heat is linked to cardiovascular stress. In fact, a 2025 study found cardiovascular failure to be the cause of most heat-related fatalities. Excessive heat is also linked with impaired kidney function and a worsening of chronic respiratory illnesses and diabetes.
Though high temperatures are usually associated with the daytime, factors like pollution and urban heat islands have contributed to warmer nights over the past decade. The body usually recovers from heat stress during the night, making warmer nights a compounding factor in heat-related illnesses. As a result, body temperature continues to rise and reaches a point that exceeds the normal temperature range, leading to heat stress.
Also read: The grave personal cost of pesticide use
It is this layered understanding of how humans experience heat that led to the development of heat indices. The simplest one is the Heat Index which considers the air temperature and humidity to give a more realistic understanding of how easily the body can cool itself through sweating.
However, the amount of heat the body absorbs and how easily it cools itself depends on many other environmental factors. So, two more advanced indices were developed: the Wet Bulb Globe Temperature (WBGT), and the Universal Thermal Climate Index (UTCI). The WBGT assesses heat using more parameters, like wind speed and solar radiation, while the UTCI takes a more interdisciplinary approach and integrates areas like thermal physiology, occupational medicine, and mathematical modelling. There are also specialised indices like the Thermal Work Limit (TWL), which is used mainly for workplace safety. It helps determine how much physical work a person can safely do in hot conditions by also considering clothing and air pressure. Though UTCI is fast gaining favour globally, India continues to rely on the Heat Index and WBGT.
The prevailing understanding is that the human threshold is a wet bulb temperature of 35°C.
All of these indices map the heat stress they measure to the corresponding physiological responses it results in, and the kind of adjustment in activity it might require. Naturally, one might wonder: how hot is too hot?
The prevailing understanding is that the human threshold is a wet bulb temperature of 35°C. Beyond this limit, even a young, healthy person seated in the shade and having access to enough drinking water would experience a continual increase in core body temperature, which will escalate to heatstroke and death within a few hours. However, some recent studies found minimally active young adults to reach thermoregulatory failure at wet bulb temperatures as low as 26°C or 31°C. More importantly, research scholars from Harvard say that—even from a purely physiological viewpoint—there is no straightforward answer. Factors like age, income, and preexisting health conditions change one’s capacity to withstand heat, posing the question: ‘too hot for whom?’.
Also read: Climate change in my cup: Why India’s cocoa and coffee production is at risk
The questions of ‘how hot is too hot?’ and ‘too hot for whom?’ similarly transfer to a sociological study of heat stress. Roughly three-quarters of India’s workforce—about 380 million people—work in occupations like agriculture and construction which have high heat exposure. Over 90 percent of the labour force works in the informal sector, with no guarantee of basic employee protections or employer liability.
This puts certain sections of society most at risk of heat stress: those who work outdoors, and the rural and urban poor. This includes construction workers, sanitation workers, street vendors, agricultural labourers, salt pan workers, delivery workers, and traffic police personnel. The rural poor, who cook on firewood stoves and walk long distances to fetch water, face prolonged, compounded heat exposure with little relief. A case study in Yavatmal, Maharashtra found that in a district where 64% of houses have tin roofs, indoor temperatures reached up to 45.8°C during peak summer hours, exceeding outdoor temperatures—meaning the home meant to shelter them only worsened their exposure. The urban poor in informal settlements face near identical conditions, where building materials trap heat and make staying indoors as dangerous as working outside. Certain occupations are also inherently more at risk, like those who work in glass or rubber factories, experiencing additional heat stress due to their workplace. Caste-based occupations, similarly, involve higher exposure to heat stress, as quantified by a 2024 IIM-B study.
The rural poor, who cook on firewood stoves and walk long distances to fetch water, face prolonged, compounded heat exposure with little relief.
Without clearly defined employee-employer relationships, it is hard to articulate how best to protect informal workers. But they are also the ones hit hardest by the absence of policies. A 2026 paper by Harvard University’s Salata Institute for Climate and Sustainability proposes coordination between various stakeholders, including worker unions, employers, governments and civil society institutions, to fasten progress. They do emphasise, however, that it would be unreasonable to expect employers to be able to fund and deliver these protections alone, and that sustainable funding mechanisms must be explored.
Environmental engineer and activist Prabhakaran Veeraarasu points out that these variations in how heat stress affects people does not reflect in the Heat Action Plans (HAPs) that cities prepare. This happens at two levels. India currently relies primarily on absolute temperature thresholds defined by the Indian Meteorological Department (IMD) for its Heat Action Plans (HAPs). Policies built on the cruder surface temperatures are working with incomplete data and will produce incomplete solutions. Notable exceptions are Thane city (since 2024), and Tamil Nadu, since earlier this month, which have both adopted a basic Heat Index instead.
The more serious concern is structural. Heat Action Plans worldwide have a tendency to lack legislative and financial backing, resulting in committees, but not change. India’s HAPs, specifically, suffer from short-sightedness; immediate measures like water coolers are not accompanied by long-term measures to increase shaded areas.
Until heat is understood not just as a weather condition but as a lived physiological and social burden, many of its worst effects will continue to go unrecognised and unprevented.
Please try another keyword to match the results
